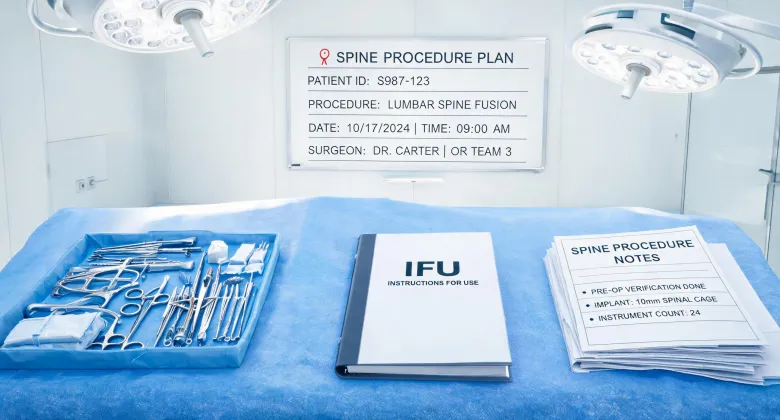
Most quality problems in surgical education aren't caught during review. They're caught in the OR, or at a training course, or in a surgeon's office when someone realizes the NuVasive XLIF surgical technique guide PDF doesn't match the current implant labeling. I've reviewed clinical education deliverables for a medical device company for years, and the pattern is consistent: the earlier you check a document against its source spec, the cheaper the fix. A five-minute verification during drafting saves an average of two and a half hours of rework before publication. Once a file goes live, the cost stops being editing time and starts being trust.
I'm the quality and brand compliance manager for that kind of company. I review every clinical education item before it reaches surgeons—roughly 200 items a year. In our Q1 2024 quality audit, I rejected 12% of first submissions because of inconsistent part numbers, outdated revision dates, or measurements that didn't match the cleared product labeling. None of those were catastrophic on their own. But they would have been, eventually.
I'm not talking about typos. A typo is annoying, but it doesn't change behavior. The quality issues that keep me up at night are the ones that could change what happens during a case: wrong implant size in a step, a measurement in millimeters where the device label uses centimeters, an old attachment reference from a system that was replaced after the merger. Those are the defects that don't show up in a spellcheck.
Why the Globus Medical NuVasive merger date is part of my checklist
One of the first things I check now is the Globus Medical NuVasive merger date. Globus Medical and NuVasive became one company when the merger closed on September 1, 2023. If you search for a NuVasive XLIF surgical technique guide PDF, you can find pre-merger versions, post-merger versions, and third-party copies that never got updated. That matters more than you'd think. A guide created before the merger may show legacy product names, old intended-use statements, or references that changed during portfolio integration.
Fifteen years ago, this was less of a problem. A technique guide was a printed booklet with a clear revision date, and the distribution list was manageable. Today, PDFs are downloaded globally from any number of places, so a small inconsistency can scale fast. The 'one file is fine' thinking comes from that print era. That's changed.
What I actually check in a technique guide
Maybe this sounds like basic housekeeping. In my experience, it's the difference between a useful guide and a liability. Here's the core checklist:
- Revision date and merger status. Is this guide still current under the Globus Medical / NuVasive portfolio?
- Implant and instrument IDs. Do the part numbers match the cleared labeling?
- Measurement accuracy. Are angles, lengths, and tolerances consistent with the instructions for use?
- Step sequence. Does it reflect the current recommended technique, not an older approach?
Four items, under five minutes. That's the cheapest insurance I know. If a guide can't pass these checks, I don't care how polished it looks. The visual design is the last thing I evaluate, not the first.
The prevention mindset applies beyond spine
Preventive verification isn't unique to spine surgery. Consider a prosthetic limb: if the residual limb is measured or cast incorrectly, the socket won't fit well, and the patient gets pressure sores or a costly remake. The measurement check before fabrication costs minutes; the re-fabrication costs weeks. Or take a vital signs monitor in a hospital setting. It has to be validated and zeroed correctly before it's trusted at the bedside, not after it generates an alarm you can't interpret. And wound care is the same story. If someone asks me what is wound care, I'd say it's mostly prevention: catch the early signs of moisture, pressure, or infection before they become a larger wound. The daily dressing change is the checklist. The inspection is the real work.
In all three cases, the professional isn't paid only for the manual action. They're paid for noticing the small detail that doesn't fit. The same is true for a technique guide reviewer. Noticing before release is where value is created.
What I learned the hard way
I didn't always believe this. In 2022, I approved a surgical technique guide after a quick scan—without checking the intended-use statement against the instructions for use. The clinical review team caught the mismatch 48 hours later, after the file had gone live and been downloaded more than 80 times. We had to pull the file, issue a corrected version, send notifications to customers, and log a corrective action. That one missing two-minute check cost me an afternoon and a chunk of credibility.
Three years earlier, I would have called that bad luck. After about 300 reviews, I've come to believe that most documentation errors are process gaps, not random mistakes. We didn't have a formal revision-check process for third-party PDFs at the time. The third time an outdated guide caused a question, I finally created a source-verification checklist. It should have been there from the start.
Where the checklist has limits
To be fair, a technique guide can't replace training, judgment, or the instructions for use. No PDF should be used as the final word on a patient-specific plan. If you are a newer surgeon, the best move is to pair the NuVasive XLIF surgical technique guide PDF with a hands-on clinical training session. The guide is a reminder, not a substitute. It tells you what the standard sequence is; it doesn't tell you what to do with unusual anatomy in front of you.
Also, checking a document doesn't make a product perfect. I've still seen edge cases where the label was clear but the surgeon's preference was different. That's okay. The goal is not to make every decision in the guide the only decision. The goal is to make sure the guide is traceable, accurate, and current before it reaches someone who is about to do something serious.
I still trust the checklist more than my memory. Five minutes of verification beats five days of correction—whether you're reviewing a surgical guide, checking a vital signs monitor, fitting a prosthetic limb, or looking at a wound during a dressing change. The tools are different, but the principle is the same: prevention is almost always cheaper than the cure.
